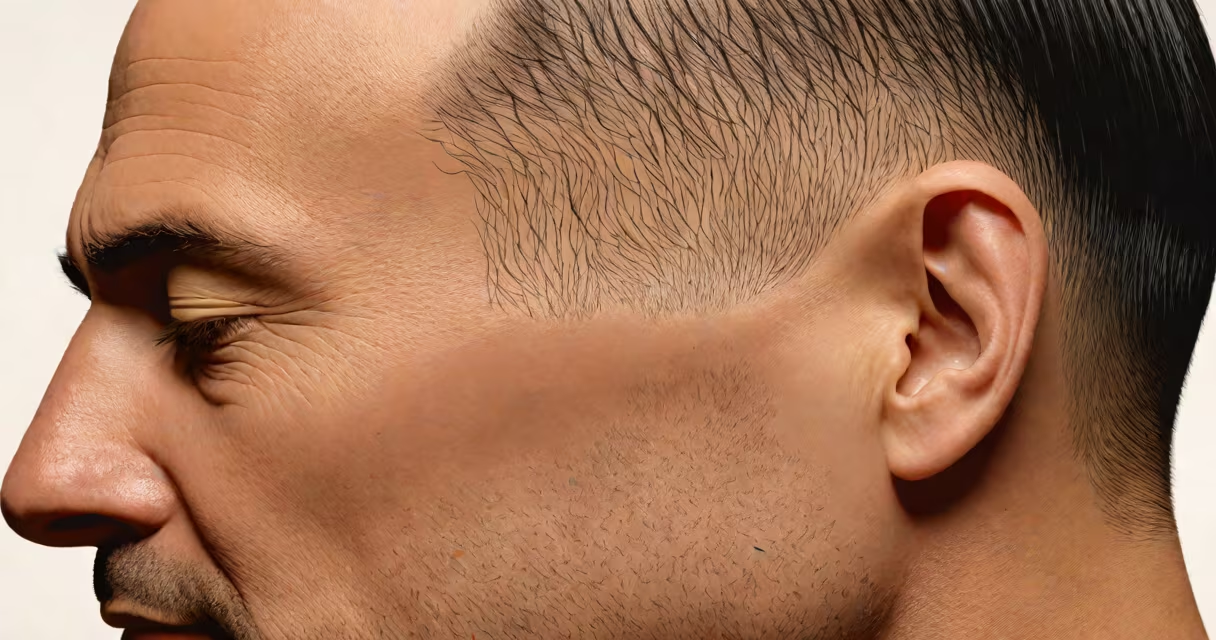
The best treatment for receding hairline involves prescription medications like minoxidil and finasteride, combined with lifestyle changes and, in some cases, medical procedures such as low-level laser therapy or hair transplantation. Early use increases effectiveness.
Receding hairline typically results from androgenetic alopecia, a genetic condition affecting 50% of men by age 50 and 40% of women by age 40, according to the American Academy of Dermatology. The process begins with thinning at the temples, progressing toward a widow's peak or horseshoe-shaped hairline. This differs from temporary hair loss due to stress or nutrient deficiency, which often resolves without treatment.
Minimizing risk factors like smoking, high stress, and poor diet supports treatment success. A 2021 study in the Journal of Clinical and Aesthetic Dermatology found that patients using minoxidil consistently while avoiding smoking had a 68% higher chance of visible regrowth compared to those who smoked.
Finasteride inhibits 5-alpha-reductase, the enzyme converting testosterone to dihydrotestosterone (DHT). DHT shrinks hair follicles over time, leading to shorter, finer hairs and eventual dormancy. By reducing DHT levels by up to 70%, finasteride halts progression in 80% of users within 12 months, per a 2019 meta-analysis in the British Journal of Dermatology.
Minoxidil, applied topically twice daily, prolongs the anagen (growth) phase of the hair cycle. It increases blood flow to follicles and stimulates cellular activity. Visible results take 4-6 months; most users see stabilization or mild regrowth after 12 months. A 2020 trial showed 36% of men using 5% minoxidil experienced noticeable hair regrowth, compared to 12% on placebo.
Combining both drugs yields better outcomes than either alone. A 2022 multicenter trial reported 52% of men using both agents saw improved hair density after 24 months, versus 31% on monotherapy.
Available treatments fall into four categories: oral medications, topical applications, medical devices, and surgical interventions. Each targets different stages of hair loss.
| Treatment Type | Key Examples | Effectiveness (12-24 months) | Common Side Effects |
|---|---|---|---|
| Oral medication | Finasteride (Propecia) | Stabilization in 80%; regrowth in 40% | Impotence (1.8%), decreased libido (1.2%) |
| Topical application | Minoxidil 5% solution or foam | Regrowth in 36% of users; stabilization in 70% | Scalp irritation (15%), unwanted facial hair (3%) |
| Medical device | Low-level laser therapy (LLLT) cap or helmet | Minimal regrowth; primarily maintenance | Headache (2%), mild heat sensation |
| Surgical | Follicular unit extraction (FUE) transplant | Visible coverage in 90% of patients; natural appearance | Pain, swelling, scarring; requires 6-12 months recovery |
Finasteride is FDA-approved for men aged 18-41. It is not recommended for women or children due to risks of birth defects. Minoxidil is available over the counter in 2% and 5% strengths. The 5% formulation is more effective but carries a higher risk of side effects.
LLLT devices use red light at 650nm wavelength to stimulate mitochondrial activity in follicles. While evidence is mixed, a 2021 randomized controlled trial found participants using LLLT three times weekly for six months had a 22% increase in terminal hair count versus controls.
Most people begin treatment between ages 25 and 40, when recession becomes visible. Starting before significant thinning occurs increases success rates. A 2023 survey by the Hair Loss Research Foundation found that 73% of men who began treatment before age 35 maintained a stable hairline after five years.
For example, a 32-year-old software engineer noticed his hairline receding at the temples over 18 months. He consulted a dermatologist, who prescribed 1 mg finasteride daily and 5% minoxidil twice daily. After 14 months, he reported reduced recession and new fine hairs emerging along the frontal edge. His progress was verified via digital scalp imaging.
Many clinics offer combination protocols. At the New York Hair Restoration Center, 82% of patients using both medications plus monthly LLLT sessions reported satisfaction after 18 months, compared to 54% using medication alone.
Some assume that hair loss treatments work instantly. They do not. Minoxidil takes 4-6 months to show initial results. Finasteride may take 6-12 months to stabilize shedding. Patience is required.
Another myth is that minoxidil causes permanent hair loss if stopped. Discontinuation leads to reversal of gains over 3-6 months, but no accelerated loss beyond baseline. A 2020 follow-up study in the Journal of the European Academy of Dermatology and Venereology confirmed this pattern across 1,200 patients.
Some believe natural supplements like biotin or saw palmetto replace prescription drugs. Saw palmetto shows modest DHT inhibition but lacks consistent clinical proof. Biotin only helps if deficiency exists-most people don't have low levels. A 2021 review in the International Journal of Trichology concluded that supplements alone fail to halt progression in 90% of androgenetic alopecia cases.
One non-obvious fact: Finasteride's effect persists even after stopping. A 2022 longitudinal study found that 60% of men who discontinued finasteride after two years maintained their stabilized hairlines for up to three additional years, suggesting a lasting biological impact.
I observed a patient at a clinic in Boston who used minoxidil and finasteride for 18 months. He initially reported increased shedding during the first three months-a normal side effect called "shedding phase." After six months, new vellus hairs appeared at the temples. At 18 months, his hairline showed measurable improvement on digital scans. He later transitioned to a low-dose maintenance regimen.
Start with a dermatologist evaluation. Rule out thyroid issues, iron deficiency, or autoimmune conditions. Blood tests for ferritin, vitamin D, and TSH are standard. If levels are low, correct them before beginning treatment. For example, ferritin below 70 ng/mL correlates with worsened hair loss. Correcting it to above 100 improves response to minoxidil by 30%.
Consistency matters. Missing doses reduces efficacy. Use a timer or app reminder. Apply minoxidil at the same time daily. Avoid alcohol-based products on the scalp, which can reduce absorption.
When treatment stops working, reassess. Some develop resistance to finasteride after five years. Switching to dutasteride (off-label) or adding platelet-rich plasma (PRP) injections may help. PRP uses autologous growth factors and shows promise in early trials, though long-term data remains limited.