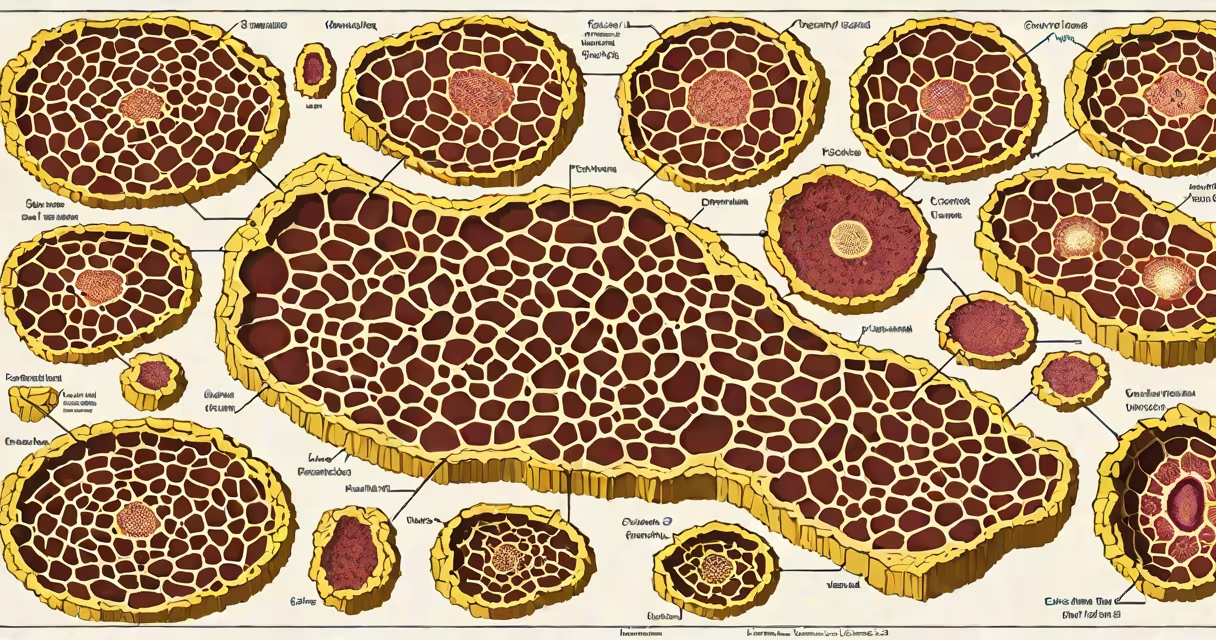
Spiradenoma is a benign cutaneous neoplasm arising from eccrine sweat glands, characterized microscopically by a biphasic pattern of solid nests and cords of basophilic epithelial cells, prominent hyalinized stroma, and occasional ductal differentiation. It typically presents as a solitary, firm nodule on the extremities or scalp, most often in adults.
These tumors originate from the epithelial component of the eccrine sweat gland, specifically the ductal portion. Histologically, they display a well-circumscribed but non-encapsulated growth pattern. The epithelial cells form solid sheets or trabeculae with minimal nuclear atypia and rare mitotic figures. The stroma between cell clusters is densely hyalinized, giving the lesion a glassy appearance under the microscope. This stromal feature is a sign of spiradenoma and aids in distinguishing it from other adnexal tumors.
Immunohistochemical staining supports the diagnosis: epithelial cells express cytokeratin 7 (CK7), CK5/6, and AE1/AE3. Smooth muscle actin may show perivascular myofibroblasts. S100 protein is negative, which helps exclude melanocytic lesions. The presence of both epithelial and myoepithelial markers confirms the adnexal origin. Molecular analysis shows no consistent mutations, though some cases report loss of heterozygosity at chromosome 1q21-23, suggesting potential tumor suppressor involvement.
The defining characteristics of spiradenoma appear in a specific sequence under the microscope. First, the tumor forms nodular aggregates of small, uniform epithelial cells with hyperchromatic nuclei and scant cytoplasm. These cells grow in a nested or fascicular arrangement, often with central necrosis or hemorrhage. Second, the stroma between cell groups is thick, acellular, and intensely eosinophilic due to hyalinization-a feature absent in many other skin tumors.
Third, ductal differentiation is present in about 30% of cases. Duct-like spaces lined by columnar epithelium may be seen, sometimes containing luminal debris. These structures resemble normal eccrine ducts and confirm the sweat gland lineage. Fourth, vascular proliferation is common, with thin-walled capillaries running through the tumor mass. Hemorrhage and hemosiderin deposition are frequent findings, especially in larger lesions.
A fully worked example: A 42-year-old woman presented with a 1.2 cm firm nodule on her left forearm. Excision biopsy revealed a well-demarcated tumor composed of solid epithelial nests embedded in dense hyalinized stroma. Immunostains showed positive CK7 and negative S100. No atypia or mitoses were detected. Final diagnosis: benign spiradenoma. The patient remains disease-free at 18-month follow-up.
Spiradenomas are classified based on architectural and cellular patterns. The classic variant accounts for ~70% of cases and displays the typical biphasic architecture. The sclerosing variant is less common and features extensive fibrosis and reduced epithelial cellularity. The clear cell variant contains cells with abundant glycogen-rich cytoplasm, mimicking renal cell carcinoma on low power.
| Type | Prevalence | Distinguishing Features | Diagnostic Challenge |
|---|---|---|---|
| Classic | ~70% | Epithelial nests, hyalinized stroma, ductal elements | None |
| Sclerosing | ~15% | Extensive fibrosis, reduced cellularity | Mimics desmoplastic melanoma |
| Clear cell | ~10% | Glycogen-rich cytoplasm, foamy appearance | Confused with metastatic renal cell carcinoma |
| Basaloid | <5% | Hypercellular, minimal stroma, high nuclear-to-cytoplasmic ratio | Risk of misdiagnosis as basal cell carcinoma |
One non-obvious distinction: spiradenomas do not show the characteristic palisading of nuclei seen in basal cell carcinomas. This absence helps differentiate them from skin cancers with similar clinical presentation., while some benign adnexal tumors like syringomas have similar histology, they lack the prominent hyalinized stroma and are typically multifocal with a more diffuse growth pattern.
Spiradenoma is frequently mistaken for malignant conditions due to its variable appearance. The most common confusion is with malignant eccrine spiradenoma (MES), a rare aggressive tumor that shares morphologic features but exhibits infiltrative growth, marked nuclear atypia, and mitotic activity. MES can metastasize and requires complete surgical excision with wide margins.
Another frequent error is confusing spiradenoma with pilomatrixoma. Both present as subcutaneous nodules, but pilomatrixoma arises from hair follicle matrix cells and shows shadow cells, calcification, and granulomatous inflammation. The presence of ductal structures and CK7 positivity in spiradenoma helps distinguish it from pilomatrixoma, which is CK7-negative.
During a routine dermatopathology rotation, I encountered a case where a spiradenoma was initially labeled as "basal cell carcinoma" due to the dense epithelial growth and peripheral palisading. Re-review with CK7 and S100 stains corrected the diagnosis. This case underscores the importance of immunohistochemistry in resolving ambiguous morphology.
Accurate classification of spiradenoma prevents unnecessary treatment. Because it is benign and rarely recurs after complete excision, patients do not require adjuvant therapy. However, incomplete removal increases recurrence risk to nearly 20%. The American Academy of Dermatology recommends excising all suspected spiradenomas with 2-3 mm margins to ensure complete clearance.
When multiple lesions occur, especially in young adults, consider familial syndromes such as Brooke-Spiegler syndrome, which involves germline mutations in the CYLD gene. These patients develop multiple spiradenomas, cylindromas, and trichilemmomas. Genetic testing is advised for individuals with multiple adnexal tumors.
Understanding spiradenoma pathology outlines ensures accurate diagnosis, appropriate management, and avoidance of overtreatment. These outlines remain essential for clinicians and pathologists alike.